اللَّهُمَّ انْفَعْنِي بِمَا عَلَّمْتَنِي، وَعَلِّمْنِي مَا يَنْفَعُنِي، وَزِدْنِي عِلْمًا“O Allah, benefit me by what You have taught me, teach me what benefits me, and increase me in knowledge.”
«رَبِّ زِدْنِي عِلْمًا»“My Lord, increase me in knowledge.” Qur’an, Ṭā-Hā 20:114 · سورة طه، الآية ١١٤
Passenger, passage, powers, position and psyche, the five interacting factors on which labour depends and which are assessed in order when progress stops.الجنين والمَمَرّ والقوى والوضعية والحالة النفسية، وهي العوامل الخمسة المتفاعلة التي يعتمد عليها المخاض، وتُقيَّم بالترتيب عند توقّف التقدّم.
Partogramمخطط المخاض (البارتوغرام)
The single sheet on which dilatation, descent, contractions, fetal heart, liquor, maternal observations, drugs and fluids are plotted against time, making the trend visible.الورقة الواحدة التي تُرسم عليها مع الزمن التوسّع والنزول والتقلّصات ومعدل قلب الجنين والسائل السلوي وقياسات الأم والأدوية والسوائل، فيتّضح بذلك الاتجاه العام.
Variabilityالتغيّرية (تغيّر معدل قلب الجنين)
The beat-to-beat fluctuation of the fetal heart rate, normally 5 to 25 beats per minute; it is the single most important feature of the trace because it reflects an intact, well-oxygenated nervous system.التذبذب بين نبضة وأخرى في معدل قلب الجنين، ويبلغ عادة ٥ إلى ٢٥ نبضة في الدقيقة؛ وهو أهم سمة منفردة في المخطط لأنه يعكس جهازاً عصبياً سليماً جيد التأكسج.
Late decelerationالتباطؤ المتأخر
A deceleration that begins after the peak of the contraction and returns to baseline after it has ended, caused by uteroplacental insufficiency; it is the most ominous of the early, variable and late decelerations, especially with reduced variability.تباطؤ يبدأ بعد ذروة التقلّص ويعود إلى الخط القاعدي بعد انتهائه، ويُعزى إلى قصور الوحدة الرحمية المشيمية؛ وهو أخطر أنواع التباطؤ الثلاثة (المبكّر والمتغيّر والمتأخّر)، ولا سيما مع انخفاض التغيّرية.
Tachysystoleفرط التقلّص
More than five contractions in ten minutes, so the uterus cannot relax and refill and placental perfusion falls; the commonest cause is too much oxytocin.أكثر من خمسة تقلّصات في عشر دقائق، فلا يستطيع الرحم الارتخاء وإعادة الامتلاء فتقلّ التروية المشيمية؛ وأشيع أسبابه الإفراط في الأوكسيتوسين.
Sinusoidal patternالنمط الجيبي
A smooth, regular wave-like oscillation of the baseline with no variability and no accelerations, suggesting severe fetal anaemia or hypoxia; it is pathological and escalated immediately.تذبذب موجي أملس منتظم للخط القاعدي دون تغيّرية ودون تسارعات، ويوحي بفقر دم شديد أو نقص أكسجة لدى الجنين؛ وهو نمط مرضي يُصعَّد أمره فوراً.
LION (intrauterine resuscitation)اختصار LION (الإنعاش داخل الرحم)
Left lateral, Intravenous fluids, Oxygen (only if she is hypoxic or per protocol), Notify and stop the oxytocin: the sequence of reversible-cause measures applied to a concerning fetal heart trace.الوضعية الجانبية اليسرى، والسوائل الوريدية، والأكسجين (فقط عند نقص أكسجة الأم أو بحسب البروتوكول المعتمد)، والإبلاغ مع إيقاف الأوكسيتوسين؛ وهي تسلسل إجراءات معالجة الأسباب القابلة للعكس عند وجود مخطط قلب جنيني مثير للقلق.
Cord prolapseتدلّي الحبل السري
The cord descending through the cervix ahead of or beside the presenting part, an emergency because it is compressed between the presenting part and the pelvis and the baby's oxygen is cut off.نزول الحبل السري عبر عنق الرحم أمام الجزء المتقدّم أو بجانبه، وهو حالة طارئة لأن الحبل ينضغط بين الجزء المتقدّم والحوض فينقطع الأكسجين عن الجنين.
Shoulder dystociaعسر ولادة الكتف
The head is born but the anterior shoulder fails to deliver behind the pubic bone, recognised by the turtle sign; fundal pressure is contraindicated and the time from head to body is recorded.ولادة الرأس مع فشل الكتف الأمامي في الخروج خلف عظم العانة، ويُعرف بعلامة السلحفاة؛ ويُمنع الضغط على قاع الرحم ويُسجَّل الزمن بين ولادة الرأس وولادة الجسم.
McRoberts manoeuvreمناورة ماكروبرتس
The first manoeuvre in shoulder dystocia: hyperflexion of the mother's hips onto her abdomen, combined with suprapubic pressure, which often resolves the dystocia on its own.المناورة الأولى في عسر ولادة الكتف، وهي فرط ثني وركَي الأم على بطنها مع الضغط فوق العانة، وكثيراً ما تحلّ العسر وحدها.
Vasa praeviaالأوعية المنزاحة (Vasa praevia)
Fetal blood vessels running unsupported through the membranes across the cervix that tear when the membranes rupture; the baby, with a tiny blood volume, can exsanguinate within minutes while the mother is well.أوعية دموية جنينية تمرّ بلا سند في الأغشية عبر عنق الرحم وتتمزّق عند تمزّق الأغشية؛ ويمكن أن ينزف الجنين، ذو الحجم الدموي الضئيل، حتى الموت خلال دقائق بينما تبقى الأم بحالة جيدة.
Active management of the third stageالتدبير الفعّال للمرحلة الثالثة من المخاض
Giving a uterotonic with or just after the birth, delayed clamping and cutting of the cord, and controlled cord traction to deliver the placenta; it shortens the third stage and substantially reduces postpartum haemorrhage.إعطاء مقبّض للرحم مع الولادة أو بعدها مباشرة، والربط المتأخر للحبل السري وقطعه، وشدّ الحبل المضبوط لإخراج المشيمة؛ وهو يقصّر المرحلة الثالثة ويقلّل النزف التالي للولادة تقليلاً كبيراً.
Progressive cervical change — the only definitive sign
Often a show, and sometimes ruptured membranes
مخاض حقيقي — تقلّصات منتظمة تطول وتقوى وتتقارب، وغالباً ما تُحَسّ في الظهر وتمتدّ حوله، ولا تُخفّفها الراحة أو المشي أو الحمّام الدافئ؛ مع تغيّر عنقي تقدّمي وهو العلامة القاطعة الوحيدة؛ وغالباً ما تظهر العلامة (سدادة المخاط المدمّاة) وأحياناً يحدث تمزّق الأغشية.
❌False labour
Contractions irregular, not progressing
Usually felt in the lower abdomen
Relieved by rest, position change or a warm bath
No cervical change
She should still be assessed, not dismissed by telephone
مخاض كاذب — تقلّصات غير منتظمة ولا تتقدّم، وتُحَسّ عادةً في أسفل البطن، وتُخفّفها الراحة أو تغيير الوضعية أو الحمّام الدافئ؛ بلا تغيّر عنقي. ومع ذلك يجب أن تُقيَّم المرأة ولا تُصرَف بالاتصال الهاتفي.
The distinction is a daily judgement, and the only definitive feature is cervical change over time — which is why a woman is assessed rather than reassured over the phone.
والتمييز حكم يومي والسمة القاطعة الوحيدة التغيّر العنقي عبر الزمن — ولهذا تُقيَّم المرأة ولا تُطمأَن هاتفياً.
Other signs include a show — the blood-stained mucus plug, which is normal and may precede labour by days — and rupture of the membranes. When the membranes rupture, one thing is done first.
علامات أخرى منها العلامة — سدادة المخاط المدمّاة وهي طبيعية وقد تسبق المخاض بأيام — وتمزّق الأغشية. وحين تتمزّق الأغشية يُفعَل أمر واحد أولاً.
1
Auscultate the fetal heart — FIRST
Rupture carries a risk of cord prolapse, and an abnormal fetal heart rate afterwards is a warning that it may have happened, although a normal rate does not exclude it.
الإصغاء لقلب الجنين أولاً — فالتمزّق يحمل خطر تدلّي الحبل وشذوذ معدّل قلب الجنين بعدئذٍ إنذار بأنه قد يكون حدث، وإن كان المعدّل الطبيعي لا ينفي ذلك.
2
Record the time
It starts the clock for infection risk.
تسجيل الوقت — يبدأ ساعة خطر العدوى.
3
Record the colour
Clear, straw-coloured, meconium-stained or blood-stained.
تسجيل اللون — صافٍ أو قشّي أو ملطّخ بالعقي أو بالدم.
4
Record the amount
And whether it is continuing to drain.
تسجيل الكمّية — وهل يستمرّ التسرّب.
5
Record the odour
An offensive smell suggests infection.
تسجيل الرائحة — فالكريهة توحي بعدوى.
•The colour of the liquor is what changes management◆ لون السائل هو ما يغيّر التدبير
Clear or straw-colouredNormal.صافٍ أو قشّي — طبيعي.
Meconium-stained — green or greenish-brownThe baby has passed meconium in utero. It may indicate fetal distress, so it raises the level of fetal monitoring — and it means the birth team prepares for possible meconium aspiration.ملطّخ بالعقي (أخضر أو بنّي مخضرّ) — طرح الجنين العقي داخل الرحم؛ وقد يدلّ على كرب جنيني فيرفع مستوى المراقبة، ويعني أن فريق الولادة يستعدّ لاحتمال استنشاق العقي.
Blood-stainedBeyond a show — consider abruption or a vasa praevia, and escalate.ملطّخ بالدم — أبعد من العلامة: يُنظر في انفصال المشيمة أو الأوعية المتقدّمة (vasa praevia) ويُصعَّد الأمر.
OffensiveSuggests chorioamnionitis — with maternal fever and a rising fetal heart rate.كريه — يوحي بالتهاب المشيماء والسلى مع حمّى أمومية وارتفاع نبض الجنين.
🔑
Memory aid
مفتاح للحفظ
The five Ps: passenger, passage, powers, position and psyche. Fear raises catecholamines which inhibit contractions, so a frightened woman genuinely labours less efficiently.
True labour contractions are regular, intensify, are felt in the back and produce cervical change. Walking usually improves true labour and settles false labour.
تقلّصات المخاض الحقيقي منتظمة وتشتدّ ويُشعَر بها في الظهر وتُحدث تغيّراً عنقياً. والمشي يحسّن الحقيقي عادةً ويُهدّئ الكاذب.
🚩
Watch out
تنبيه
The first action after membranes rupture is to listen to the fetal heart, because the greatest risk at that moment is cord prolapse. Record the time, colour, amount and odour.
أول إجراء بعد تمزّق الأغشية الإصغاء لقلب الجنين، فأعظم خطر تلك اللحظة تدلّي الحبل. ويُسجَّل الوقت واللون والكمّية والرائحة.
⭐
Key point
نقطة أساسية
Meconium-stained liquor may indicate fetal distress and creates a risk of meconium aspiration, so the fetus is monitored more closely and the neonatal team is alerted before the birth.
السائل الملوّث بالعقي قد يدلّ على كرب جنيني ويخلق خطر استنشاق العقي، فيُراقَب الجنين عن كثب أكثر ويُنبَّه فريق الولدان قبل الولادة.
3
5.2 · The Stages of Labour and How Progress Is Assessed٥٫٢ · مراحل المخاض وكيف يُقيَّم التقدّم
The stages of labour — first stage to full dilatation, second to birth of the baby, third to delivery of the placentaمراحل المخاض — الأولى حتّى التوسّع الكامل والثانية حتّى ولادة الطفل والثالثة حتّى خروج المشيمةنص المخطط: مراحل المخاض — ١. الأولى: من البدء إلى التوسّع الكامل (١٠ سم)؛ ٢. الثانية: من التوسّع الكامل إلى ولادة الطفل (الدفع)؛ ٣. الثالثة: من ولادة الطفل إلى خروج المشيمة (مقلّص للرحم)؛ ٤. الرابعة: الساعات الأولى بعد الولادة (المراقبة).Educational schematic (AL-FAHAD diagram, not a patient image) · مخطط تعليمي توضيحي وليس صورة لمريض
Labour is divided into four stages.
يُقسَم المخاض إلى أربع مراحل.
1
First stage — onset to full dilatation
Latent phase: the cervix effaces and dilates slowly to around 5–6 cm. Active phase: dilatation becomes more rapid and predictable.
المرحلة الأولى — من البدء إلى التوسّع الكامل: طور كامن يمّحي فيه عنق الرحم ويتّسع ببطء حتى نحو ٥ إلى ٦ سم، ثم طور نشط يصير فيه التوسّع أسرع وأكثر قابلية للتنبّؤ.
2
Second stage — full dilatation to birth
A passive part, where the head descends without pushing, and an active part where she pushes.
الثانية — من التوسّع الكامل إلى الولادة: جزء سلبي ينزل فيه الرأس دون دفع وجزء نشط تدفع فيه الأمّ.
3
Third stage — birth to placenta
Delivery of the placenta and membranes.
الثالثة — من الولادة إلى خروج المشيمة: خروج المشيمة والأغشية.
4
Fourth stage — the first hours after
The immediate recovery period, where haemorrhage is watched for.
الرابعة — الساعات الأولى بعدها: فترة التعافي الفورية حيث يُترقَّب النزف.
Contractions are described by three things — and the third is the one that is done wrongly.
التقلّصات تُوصَف بثلاثة أمور — والثالث هو الذي يُفعَل خطأً.
Frequencyhow many in ten minutesالتواتر — كم في عشر دقائق
Durationtimed from the start to the end of eachالمدّة — من بداية كلّ تقلّص إلى نهايته
Strengthassessed by palpation — not by the number on the machineالقوّة — بالجسّ لا برقم الجهاز
The monitor records the frequency and duration reliably; it does not measure strength. A tocograph tracing tall peaks in a woman whose uterus feels soft is telling you about the transducer, not the contraction.
فالجهاز يسجّل التواتر والمدّة بموثوقية؛ ولا يقيس القوّة. والمخطّط الذي يرسم قمماً عالية في امرأة رحمها يبدو ليّناً يدلّ على حال المجسّ لا على التقلّص.
A vaginal examination establishes several things at once, and it is worth being able to list them.
الفحص المهبلي يحدّد عدّة أمور في آنٍ ويستحقّ القدرة على سردها.
1
Dilatation
The cervix in centimetres.
التوسّع — العنق بالسنتيمترات.
2
Effacement
How thin and drawn up the cervix has become.
الانمحاء — كم صار العنق رقيقاً ومسحوباً.
3
Consistency and position
Firm or soft; posterior, mid or anterior.
القوام والموضع — قاسٍ أم ليّن؛ خلفي أم متوسّط أم أمامي.
4
Presenting part and station
What is presenting, and how far down relative to the ischial spines.
الجزء المتقدّم والمحطّة — ما يجيء وكم نزل نسبةً للشوكتين الإسكيّتين.
5
Position of the head
Determined from the sutures and fontanelles.
موقع الرأس — يُحدَّد من الدروز واليافوخين.
6
Caput and moulding
Which indicate how much the head has been compressed.
الورم الرأسي (caput) والتشكّل — يدلّان على مدى انضغاط الرأس.
7
Membranes and liquor
Intact or ruptured, and the colour if draining.
الأغشية والسائل — سليمة أم متمزّقة واللون إن كان يتسرّب.
The partogram is the single sheet on which all of it is plotted against time — dilatation, descent, contractions, the fetal heart, the liquor, maternal observations, drugs and fluids. Its value is that it makes the trend visible: a graph that has flattened says something a column of numbers does not, and it says it to whoever picks up the notes next.
مخطّط المخاض هو الورقة الواحدة التي يُرسَم عليها كلّ ذلك مقابل الزمن — التوسّع والنزول والتقلّصات وقلب الجنين والسائل وقياسات الأمّ والأدوية والسوائل. وقيمته أنه يجعل الاتّجاه مرئياً: فالمنحنى الذي استوى يقول شيئاً لا يقوله عمود أرقام ويقوله لمن يتسلّم السجلّات لاحقاً.
🔑
Memory aid
مفتاح للحفظ
First stage: onset to full dilatation at ten centimetres. Second: full dilatation to birth. Third: birth to delivery of the placenta. Fourth: the first hours after, when haemorrhage most often occurs.
المرحلة الأولى: من البدء إلى التوسّع الكامل عند عشرة سنتيمترات. والثانية: من التوسّع الكامل إلى الولادة. والثالثة: من الولادة إلى خروج المشيمة. والرابعة: الساعات الأولى بعدها حين يحدث النزف غالباً.
⭐
Key point
نقطة أساسية
Assess contraction strength by palpation rather than by what the machine draws — a tocograph records the shape of a contraction but not its power.
تُقيَّم قوّة التقلّص بالجسّ لا بما يرسمه الجهاز — فمخطّط التقلّص يسجّل شكل التقلّص لا قوّته.
🔑
Memory aid
مفتاح للحفظ
Station is measured from the ischial spines: level with them is zero, above is negative, below is positive. Plus two means two centimetres below the spines.
المحطّة تُقاس من الشوكتين الإسكيّتين: فمستواهما صفر وفوقهما سالب وتحتهما موجب. وزائد اثنين تعني سنتيمترين تحتهما.
⭐
Key point
نقطة أساسية
Plot the partogram contemporaneously. One filled in from memory at the end of a shift is a document rather than a monitoring tool.
يُرسَم مخطّط المخاض في حينه. فالمملوء من الذاكرة في نهاية المناوبة وثيقة لا أداة مراقبة.
4
5.3 · Examining Her, Watching Her, and When Progress Stops٥٫٣ · فحصها ومراقبتها وحين يتوقّف التقدّم
A vaginal examination is an intimate examination, and being in labour does not remove the requirement for consent.
الفحص المهبلي فحص حميم وكونها في مخاض لا يُلغي اشتراط الموافقة.
1
Explain what and why
What you propose to do, and why it is needed now.
شرح ماذا ولماذا — ما يُقترَح فعله ولماذا يلزم الآن.
2
Say what you will be feeling for
It is less frightening when she knows.
بيان ما سيُبحَث عنه — أقلّ إخافةً حين تعرف المرأة.
3
Seek agreement for THIS examination
Not relying on one given at admission.
طلب الموافقة لهذا الفحص — دون الاعتماد على موافقة أُعطيت عند الدخول.
4
Offer a chaperone; ensure privacy
Cover her; manage who is in the room.
عرض مرافق وضمان الخصوصية — تغطيتها وإدارة من في الغرفة.
5
Stop if she asks you to
Withdrawal of consent applies mid-procedure. A woman in labour who says stop is not negotiating.
التوقّف إن طلبت المرأة ذلك — فسحب الموافقة ينطبق في منتصف الإجراء، والمرأة في المخاض التي تطلب التوقّف لا تفاوض.
How often matters too, and more is not better. In established labour, roughly every four hours or sooner if clinically indicated is the usual pattern — a change in the contractions, an urge to push, ruptured membranes, a concern about the fetal heart, or before giving analgesia. Each examination carries an infection risk and each is intrusive, so a nurse should be able to say why this one is being done.
ويهمّ كذلك عدد مرّات الفحص، فالأكثر ليس أفضل. ففي المخاض المستقرّ يكون النمط المعتاد نحو كلّ أربع ساعات أو أبكر إن استُطبّ سريرياً — عند تغيّر التقلّصات، أو الرغبة في الدفع، أو تمزّق الأغشية، أو القلق على قلب الجنين، أو قبل إعطاء مسكّن. ولكلّ فحص خطر عدوى وكلّ فحص اقتحامي، فينبغي أن يكون بمقدور الممرّض أو الممرّضة بيان سبب إجراء هذا الفحص.
Maternal observations run alongside the fetal ones and are easy to let slip when attention is on the trace. Pulse, blood pressure, temperature and respiratory rate at the protocol frequency — more often with risk factors, oxytocin, an epidural, or any concern. Note that a rising maternal pulse is one of the earliest signs of both haemorrhage and sepsis, and it is on the same chart everyone is already looking at.
قياسات الأمّ تجري إلى جانب الجنينية ويسهل إغفالها حين يكون الانتباه على المخطّط. النبض والضغط والحرارة ومعدّل التنفّس بتواتر البروتوكول — أكثر مع عوامل الخطر أو الأوكسيتوسين أو فوق الجافية أو أيّ قلق. ويُلاحَظ أن ارتفاع نبض الأمّ من أبكر علامات النزف والإنتان معاً وهو على المخطّط نفسه الذي ينظر إليه الجميع.
•Sepsis in labour — easy to attribute to labour itself◆ الإنتان في المخاض — يسهل أن يُعزى إلى المخاض نفسه
Maternal fever, tachycardia, rigorsAnd a general sense of being unwell.حمّى أمومية وتسرّع قلب وقشعريرة مع شعور عام بالإعياء.
Offensive or discoloured liquorWith uterine tenderness.سائل كريه أو متغيّر اللون مع إيلام رحمي.
A rising fetal heart rateFetal tachycardia can be the first sign of maternal sepsis — the baby responds before she does.ارتفاع نبض الجنين — قد يكون تسرّع قلب الجنين أول علامة لإنتان الأمّ، فالجنين يستجيب قبلها.
And it can present without a high temperatureA woman who is simply ‘not right’ with a rising pulse is escalated, not reassured.وقد يتظاهر بلا حرارة مرتفعة — فالمرأة التي «ليست على ما يرام» مع نبض متزايد تُصعَّد حالتها ولا تُطمأَن.
When progress stops, the assessment follows the same three headings as everything else in this chapter.
حين يتوقّف التقدّم يتبع التقييم العناوين الثلاثة نفسها كما في كلّ شيء في هذا الفصل.
1
Powers
Are the contractions strong, long and frequent enough? Palpate — do not read the machine.
القوى — هل التقلّصات قوية وطويلة ومتواترة كفايةً؟ يُجَسّ الرحم ولا يُعتمَد على قراءة الجهاز.
2
Passenger
Position, presentation, attitude, size — is a malposition the obstruction?
الراكب — الموقع والمجيء والانثناء والحجم: هل سوء الموقع هو العائق؟
3
Passage
The pelvis, and any soft tissue obstruction — including a full bladder.
الممرّ — الحوض وأيّ عائق في الأنسجة الرخوة بما في ذلك المثانة الممتلئة.
4
And the two others
Position — is she upright and mobile? Psyche — is she frightened, exhausted or unsupported?
والاثنان الآخران — الوضعية: هل هي منتصبة متحرّكة؟ والنفسية: هل هي خائفة أو منهكة أو بلا دعم؟
The last two are the ones skipped, and they are often the answer: a woman who is frightened, flat on her back, with a full bladder and no support has three correctable causes of delay before anyone reaches for oxytocin.
والأخيران هما المتخطّيان وهما الجواب غالباً: فالمرأة الخائفة المستلقية على ظهرها بمثانة ممتلئة وبلا دعم لديها ثلاثة أسباب قابلة للتصحيح للتأخّر قبل أن يمدّ أحد يده للأوكسيتوسين.
🚩
Watch out
تنبيه
Being in labour does not remove the requirement for consent. Seek agreement for each vaginal examination rather than relying on one given at admission, and stop if she asks.
كونها في المخاض لا يُلغي شرط الموافقة. تُطلَب الموافقة على كلّ فحص مهبلي ولا يُعتمَد على موافقة أُعطيت عند التنويم، ويُتوقَّف إن طلبت المرأة ذلك.
⭐
Key point
نقطة أساسية
Examine roughly four-hourly in established labour or sooner if indicated. Each examination carries an infection risk, and examining more often does not make labour faster.
يُجرى الفحص نحو كلّ أربع ساعات في المخاض المستقرّ أو أبكر إن استُطبّ. فكلّ فحص يحمل خطر عدوى والفحص الأكثر تواتراً لا يجعل المخاض أسرع.
🚩
Watch out
تنبيه
Sepsis can present with a normal or even low temperature, so its absence excludes nothing. A woman who is simply not herself is a described feature of sepsis.
الإنتان قد يتظاهر بحرارة طبيعية أو حتى منخفضة فغيابها لا يستبعد شيئاً. والمرأة التي ليست على طبيعتها ببساطة سمة موصوفة للإنتان.
⭐
Key point
نقطة أساسية
A woman who is exhausted, dehydrated, frightened or in uncontrolled pain does not contract effectively. Treating that is treatment of the delay, not a comfort measure.
المرأة المُنهكة أو المصابة بالجفاف أو الخائفة أو في ألم غير مضبوط لا تتقلّص بفعالية. ومعالجة ذلك علاج للتأخّر لا تدبير راحة.
⭐
Key point
نقطة أساسية
Cephalopelvic disproportion is diagnosed during labour rather than predicted before it, which is why a previous large baby or a small stature is not a reason to bypass labour.
يُشخَّص عدم تناسب الرأس والحوض أثناء المخاض ولا يُتنبَّأ به قبله، ولهذا لا تكون ولادة طفل كبير سابقة أو قصر القامة سبباً لتجاوز المخاض.
5
5.4 · How the Baby Moves Through, and Pain in Labour٥٫٤ · كيف يمرّ الطفل والألم في المخاض
The baby negotiates the pelvis through a sequence of movements, and understanding them explains much of what is felt on examination.
يجتاز الطفل الحوض عبر سلسلة من الحركات، وفهمها يفسّر كثيراً ممّا يُحَسّ عند الفحص.
1
Engagement
The widest part of the head passes the pelvic brim.
الانخراط — أعرض جزء من الرأس يعبر مدخل الحوض.
2
Descent
Continuing throughout.
النزول — مستمرّ طوال الوقت.
3
Flexion
The chin is pushed onto the chest — this presents the smallest diameter.
الانثناء — يُدفَع الذقن نحو الصدر فيقدّم أصغر قطر.
4
Internal rotation
The head turns so the occiput comes to the front.
الدوران الداخلي — يدور الرأس فيأتي القذال للأمام.
5
Extension
The head is born by extending under the symphysis.
البسط — يُولَد الرأس ببسطه تحت الارتفاق.
6
Restitution and external rotation
The head realigns with the shoulders.
الاسترداد والدوران الخارجي — يعود الرأس لمحاذاة الكتفين.
7
Expulsion
The shoulders and body follow.
الطرد — يتبع الكتفان والجسم.
Pain relief begins with what does not involve a drug, and these are genuinely effective rather than a preamble.
يبدأ تسكين الألم بما لا يتضمّن دواءً وهذه فعّالة فعلاً لا تمهيداً.
•Non-pharmacological — and the evidence is better than you expect◆ غير دوائي — والأدلّة أفضل ممّا يُتوقَّع
Continuous one-to-one supportBetter evidence behind it than most interventions in this chapter — shorter labour, less analgesia, fewer operative births.دعم فردي مستمرّ — دليله أفضل من معظم تدخّلات هذا الفصل: مخاض أقصر وتسكين أقلّ وولادات جراحية أقلّ.
Freedom to move and change positionShortens labour and reduces the need for analgesia.حرّية الحركة وتغيير الوضعية — تقصّر المخاض وتقلّل الحاجة للتسكين.
Water immersion, heat, massageEffective for many women and carry no added fetal risk provided the water stays at or below 37.5 °C and the woman’s temperature is checked hourly.الغمر بالماء والحرارة والتدليك — فعّالة لكثيرات ولا تضيف خطراً على الجنين ما دامت حرارة الماء لا تتجاوز ٣٧٫٥ °م وتُفحَص حرارة الأمّ كل ساعة.
Breathing and a calm environmentFear raises adrenaline, and adrenaline slows labour — physiology, not comfort.التنفّس وبيئة هادئة — فالخوف يرفع الأدرينالين والأدرينالين يبطئ المخاض؛ وهذه فيزيولوجيا لا مجرّد راحة.
Inhaled analgesia — nitrous oxide with oxygen — is self-administered, works within seconds and wears off within seconds. That is exactly why it is safe: she cannot over-sedate herself, because she would drop the mouthpiece. Teach her to start breathing it as the contraction begins, not at its peak, so the effect arrives when the pain does.
التسكين المستنشَق — أكسيد النيتروز مع الأكسجين — ذاتي الإعطاء، يعمل خلال ثوانٍ ويزول خلال ثوانٍ. وهذا بالضبط سبب أمانه: فلا تستطيع المرأة الإفراط في تهدئة نفسها لأنها ستُسقط قطعة الفم. وتُعلَّم المرأة البدء بتنفّسه مع بداية التقلّص لا عند ذروته ليصل أثره حين يصل الألم.
An epidural gives the most complete pain relief available, and its main risk is maternal hypotension: the block causes vasodilatation, the blood pressure falls, and placental perfusion falls with it — so the fetal heart rate can deteriorate. The nursing care follows directly from that.
فوق الجافية يعطي أكمل تسكين متاح وخطره الرئيس هبوط ضغط الأمّ: فالحصار يسبّب توسّعاً وعائياً ويهبط الضغط وتهبط تروية المشيمة معه — فقد يتدهور نبض الجنين. والرعاية التمريضية تترتّب مباشرةً على ذلك.
1
Before — intravenous access and a fluid preload
Per your protocol, and a baseline blood pressure.
قبل — مدخل وريدي وتحميل سوائل مسبق حسب البروتوكول وقياس ضغط أساسي.
2
During and after — blood pressure frequently
Most closely in the first period after insertion and after any top-up.
أثناء وبعد — الضغط بتواتر، وبمراقبة أوثق في الفترة الأولى بعد الإدخال وبعد أيّ جرعة إضافية.
3
If it falls — turn her to the left
Relieves aortocaval compression; give fluids and call the anaesthetist.
إن هبط — تُدار المرأة إلى جهة اليسار: يزيل ذلك الضغط على الأبهر والأجوف؛ وتُعطى السوائل ويُستدعى طبيب التخدير.
4
Continuous fetal monitoring
Because the fetal heart is the first thing to show the drop.
مراقبة جنينية مستمرّة — فنبض الجنين أول ما يُظهر الهبوط.
•The rest is the consequences of a numb lower body◆ والباقي من نتائج خدر النصف السفلي من الجسم
Bladder sensation is lostShe is encouraged to void regularly or catheterised as prescribed — a full bladder is uncomfortable, obstructs descent, and can be injured.فقد إحساس المثانة — تُشجَّع المرأة على التبوّل بانتظام أو تُجرى لها قسطرة بولية حسب الوصفة؛ فالمثانة الممتلئة مزعجة وتعيق النزول وقد تتأذّى.
Her legs are weakShe does not stand unaided, and is assisted with every position change.ساقاها ضعيفتان — لا تقف المرأة بلا مساعدة وتُساعَد عند كلّ تغيير للوضعية.
Pressure areasShe cannot feel discomfort, so position is changed regularly for her.مناطق الضغط — لا تشعر المرأة بالانزعاج، فتُغيَّر وضعيتها بانتظام.
Pushing may be less effectiveThe urge is reduced — which is why a passive second stage is often allowed before active pushing.الدفع قد يكون أقلّ فعالية — فالرغبة تقلّ، ولذلك يُسمَح غالباً بمرحلة ثانية سلبية قبل الدفع الفعّال.
🔑
Memory aid
مفتاح للحفظ
A well-flexed head presents its smallest diameter. The cardinal movements are engagement, descent, flexion, internal rotation, extension, restitution, external rotation and expulsion.
الرأس جيّد الانثناء يقدّم أصغر قطر له. والحركات الأساسية: الانخراط والنزول والانثناء والدوران الداخلي والبسط والاسترداد والدوران الخارجي والطرد.
⭐
Key point
نقطة أساسية
Continuous one-to-one support has better evidence behind it than most interventions in this chapter, and freedom to move shortens labour and reduces the need for other analgesia.
الدعم المستمرّ فرد لفرد له أدلّة أفضل من معظم تدخّلات هذا الفصل، وحرّية الحركة تقصّر المخاض وتقلّل الحاجة لمسكّنات أخرى.
🚩
Watch out
تنبيه
The main risk of an epidural is maternal hypotension, which reduces placental perfusion and can deteriorate the fetal heart rate. Check the bladder is empty before, and monitor blood pressure frequently after.
الخطر الرئيس لفوق الجافية هبوط ضغط الأمّ الذي يقلّل تروية المشيمة وقد يُدهور معدّل قلب الجنين. يُتحقَّق من فراغ المثانة قبله ويُراقَب الضغط بتواتر بعده.
⭐
Key point
نقطة أساسية
Opioid given to the mother crosses the placenta and can cause neonatal respiratory depression and a baby slow to feed, so timing matters and the neonatal team is informed.
الأفيوني المُعطى للأمّ يعبر المشيمة وقد يسبّب تثبيطاً تنفّسياً وليدياً وطفلاً بطيء الرضاعة، فالتوقيت يهمّ ويُبلَّغ فريق الولدان.
🚩
Watch out
تنبيه
With an epidural she cannot feel her bladder, her legs, pressure or heat — so void regularly, change position, check heels and sacrum, and place nothing hot against her.
مع فوق الجافية لا تشعر بمثانتها ولا ساقيها ولا الضغط ولا الحرارة — فيلزم تشجيعها على التبوّل بانتظام وتغيير وضعيتها وفحص الكعبين والعجز وعدم وضع أي شيء ساخن عليها.
6
5.5 · Reading a Fetal Heart Trace٥٫٥ · قراءة تخطيط قلب الجنين
A cardiotocograph trace — fetal heart rate above, uterine contractions below. Decelerations are classified by their TIMING relative to the contraction beneath themتخطيط القلب والتقلّصات (CTG) — معدّل قلب الجنين فوق وتقلّصات الرحم تحت؛ وتُصنّف التباطؤات بتوقيتها نسبةً للتقلّص تحتهانص المخطط: معدّل قلب الجنين؛ التقلّصات. التباطؤات المتأخّرة — أدنى نقطة تأتي بعد ذروة التقلّص.Educational schematic (AL-FAHAD diagram, not a patient image) · مخطط تعليمي توضيحي وليس صورة لمريض
👂Intermittent auscultation
Hand-held Doppler or Pinard, at defined intervals
During and immediately after a contraction
For a woman at low risk
Keeps her mobile — which itself helps labour
Fewer false alarms and fewer unnecessary interventions
الإصغاء المتقطّع — بجهاز دوبلر يدوي أو سمّاعة بينارد (Pinard) بفواصل محدّدة، أثناء التقلّص وبعده مباشرةً، للمرأة منخفضة الخطر؛ يُبقيها متحرّكة وهذا بحدّ ذاته يساعد المخاض، وفيه إنذارات كاذبة وتدخّلات غير ضرورية أقلّ.
📈Continuous CTG
For defined risk factors — oxytocin, epidural, meconium, bleeding, maternal illness
Or when auscultation raises a concern
Records the pattern over time
Restricts mobility and raises intervention rates
Not better for low-risk women
المراقبة المستمرّة (CTG) — لعوامل خطر محدّدة: الأوكسيتوسين أو فوق الجافية أو العقي أو النزف أو مرض الأمّ، أو حين يثير الإصغاء قلقاً؛ تسجّل النمط عبر الزمن، لكنها تقيّد الحركة وترفع معدّلات التدخّل، وليست أفضل للنساء منخفضات الخطر.
Read every trace the same way, in the same order. A widely used framework is DR C BRAVADO.
يُقرَأ كلّ مخطّط بالطريقة نفسها والترتيب نفسه. وإطار واسع الاستخدام DR C BRAVADO.
1
DR — Define Risk
What is the clinical picture? A trace is interpreted in the context of the woman, never in isolation.
تحديد الخطر — ما الصورة السريرية؟ فالمخطّط يُفسَّر في سياق المرأة ولا يُفسَّر أبداً بمعزل عنها.
2
C — Contractions
How many in ten minutes.
التقلّصات — كم في عشر دقائق.
3
BRA — Baseline Rate
Normal 110–160 beats per minute.
المعدّل الأساسي — طبيعي ١١٠ إلى ١٦٠ نبضة في الدقيقة.
4
V — Variability
Beat-to-beat fluctuation, normally 5–25. The single most important feature.
التغيّرية — تذبذب من نبضة لنبضة وطبيعي ٥ إلى ٢٥: أهمّ سمة منفردة.
5
A — Accelerations
Rises of 15 beats for 15 seconds — reassuring.
التسارعات — ارتفاع ١٥ نبضة لمدّة ١٥ ثانية: مطمئنة.
6
D — Decelerations
The type matters far more than the presence.
التباطؤات — النوع يهمّ أكثر بكثير من الوجود.
7
O — Overall impression
Classify the trace as a whole and decide what happens next.
الانطباع العامّ — تصنيف المخطّط ككلّ وتقرير ما يلي.
Variability is the most important feature because it reflects an intact and well-oxygenated nervous system. Reduced variability for a prolonged period is more concerning than most decelerations, and it is the feature most often under-weighted.
التغيّرية أهمّ سمة لأنها تعكس جهازاً عصبياً سليماً وحسن الأكسجة. وانخفاضها لمدّة مطوّلة أدعى للقلق من معظم التباطؤات، وهي السمة التي يُقلَّل من شأنها في الغالب.
Decelerations are where the examinable discrimination lies, and VEAL CHOP pairs each with its cause.
التباطؤات هي موضع التمييز الذي يُمتحَن فيه، ويقرن إطار VEAL CHOP كلّاً منها بسببه.
📋VEAL
Variable
Early
Accelerations
Late
متغيّرة ومبكّرة وتسارعات ومتأخّرة.
➡️CHOP
Cord compression
Head compression — benign
Okay
Placental insufficiency
انضغاط الحبل، وانضغاط الرأس — حميد، وبخير، وقصور مشيمي.
•The three decelerations in detail◆ التباطؤات الثلاثة بالتفصيل
Early — head compressionMirror the contraction: begin with it, trough at its peak, recover as it ends. Physiological and benign.مبكّرة — انضغاط الرأس: تعكس التقلّص فتبدأ معه وتبلغ قاعها عند ذروته وتتعافى مع انتهائه، وهي فيزيولوجية حميدة.
Variable — cord compressionVary in shape and timing. Often related to cord compression; may respond to a change of maternal position.متغيّرة — غالباً انضغاط الحبل: تتباين شكلاً وتوقيتاً وقد تستجيب لتغيير وضعية الأمّ.
Late — placental insufficiencyBegin after the peak and return to baseline after the contraction has ended — the dip is shifted to the right. Caused by uteroplacental insufficiency: the placenta cannot meet the baby’s oxygen demand during a contraction.متأخّرة — قصور مشيمي: تبدأ بعد الذروة وتعود إلى الأساس بعد انتهاء التقلّص فالانخفاض منزاح لليمين. سببها قصور رحمي مشيمي: فالمشيمة لا تلبّي حاجة الجنين من الأكسجين أثناء التقلّص.
Late decelerations matter most, and the timing is the whole discrimination: an early deceleration mirrors the contraction; a late one is shifted right. That shift is not a detail — it is the difference between a benign reflex and a baby who is not being oxygenated.
التباطؤات المتأخّرة أهمّها والتوقيت هو التمييز كلّه: فالمبكّرة تعكس التقلّص والمتأخّرة منزاحة لليمين. وذلك الانزياح ليس تفصيلاً — بل الفرق بين منعكس حميد وطفل لا تجري أكسجته.
🔑
Memory aid
مفتاح للحفظ
DR C BRAVADO: Define Risk, Contractions, Baseline Rate, Variability, Accelerations, Decelerations, Overall. The last letter matters most — the commonest failure is reading a trace correctly and not acting.
DR C BRAVADO: تحديد الخطر والتقلّصات والمعدّل الأساس والتغيّرية والتسارعات والتباطؤات والانطباع العامّ. والحرف الأخير الأهمّ — فأشيع أشكال الإخفاق قراءة التخطيط قراءةً صحيحة ثم عدم التصرّف.
🔑
Memory aid
مفتاح للحفظ
VEAL CHOP: Variable with Cord compression, Early with Head compression, Accelerations Okay, Late with Placental insufficiency.
VEAL CHOP: المتغيّر مع انضغاط الحبل والمبكّر مع انضغاط الرأس والتسارعات بخير والمتأخّر مع قصور المشيمة.
🚩
Watch out
تنبيه
Late decelerations begin after the peak of the contraction and are caused by uteroplacental insufficiency. They are a worrying pattern, especially when repetitive or with reduced variability — though a sinusoidal trace, an acute bradycardia, or recurrent decelerations with absent variability are more ominous still.
التباطؤات المتأخّرة تبدأ بعد ذروة التقلّص ويسبّبها قصور رحمي مشيمي. وهي نمط مقلق خاصّةً حين تتكرّر أو مع نقص التغيّرية، وإن كان النمط الجيبي أو بطء القلب الحادّ أو التباطؤات المتكرّرة مع غياب التغيّرية أشدّ إنذاراً.
⭐
Key point
نقطة أساسية
Variability of 5 to 25 beats per minute reflects an intact and well-oxygenated nervous system. Reduced variability may simply be a sleep cycle, opioids or magnesium — but not if it persists or comes with anything else.
التغيّرية من ٥ إلى ٢٥ ضربة في الدقيقة تعكس جهازاً عصبياً سليماً جيّد الأكسجة. ونقصها قد يكون مجرّد دورة نوم أو أفيونيات أو مغنيسيوم — لكن ليس إن استمرّ أو رافقه شيء آخر.
🚩
Watch out
تنبيه
Tachysystole is more than five contractions in ten minutes. The uterus cannot relax and refill, so placental perfusion falls — and the commonest cause is too much oxytocin.
فرط التقلّص أكثر من خمسة تقلّصات في عشر دقائق. فلا يستطيع الرحم الارتخاء وإعادة الامتلاء فتهبط تروية المشيمة — وسببه الأشيع أوكسيتوسين أكثر من اللازم.
7
5.6 · Classifying a Trace, and the Trace That Is Not the Baby٥٫٦ · تصنيف التخطيط والتخطيط الذي ليس للطفل
Once the features are described, the trace is classified as a whole — because it is the classification, not any single feature, that determines what happens next.
بمجرّد وصف السمات يُصنَّف المخطّط ككلّ — فالتصنيف لا أيّ سمة منفردة هو ما يحدّد ما يلي.
1
Normal
All features reassuring. Continue as you are.
طبيعي — كلّ السمات مطمئنة: تُواصَل الرعاية كما هي.
2
Suspicious
One non-reassuring feature. Correct the reversible causes and watch closely.
مشبوه — سمة واحدة غير مطمئنة: تُصحَّح الأسباب القابلة للعكس وتُراقَب الحالة عن كثب.
3
Pathological
Two or more non-reassuring, or one abnormal feature. Escalate and prepare for a decision.
مرضي — اثنتان أو أكثر غير مطمئنة أو واحدة شاذّة: يُصعَّد الأمر ويُستعَدّ لاتخاذ قرار.
4
Need for urgent intervention
Act now. Acute bradycardia or a prolonged deceleration beyond the action threshold — this category is not a description, it is an instruction.
حاجة لتدخّل عاجل — يُتصرَّف الآن: بطء قلب حادّ أو تباطؤ مطوّل يتجاوز عتبة الإجراء؛ وهذه الفئة تعليمة لا وصف.
A prolonged deceleration has two numbers, and conflating them is dangerous.
التباطؤ المطوّل له رقمان وخلطهما خطر.
≥15 beatsthe size of the fall١٥ نبضة أو أكثر — حجم الانخفاض
2–10 minthe definition٢ إلى ١٠ دقائق — التعريف
3 minthe point at which it demands urgent action٣ دقائق — النقطة التي تستدعي إجراءً عاجلاً
So a deceleration of three minutes is still within the definition and already past the action threshold. Waiting to see whether it reaches ten minutes is the error.
فالتباطؤ الذي يدوم ثلاث دقائق ما زال ضمن التعريف وقد تجاوز أصلاً عتبة الإجراء. والانتظار لمعرفة ما إذا كان سيبلغ عشر دقائق هو الخطأ.
•The sinusoidal pattern — rare, easy to miss, and specific◆ النمط الجيبي — نادر، ويسهل إغفاله، ونوعي
What it looks likeA smooth, regular, wave-like oscillation of the baseline with no beat-to-beat variability and no accelerations. It looks almost too regular — like a drawn wave rather than a recording.الشكل — تذبذب موجي أملس منتظم لخطّ الأساس بلا تغيّرية من نبضة لنبضة ولا تسارعات: يبدو منتظماً أكثر ممّا ينبغي، كموجة مرسومة لا كتسجيل.
What it meansSevere fetal anaemia or hypoxia — for example fetomaternal haemorrhage or rhesus disease.المعنى — فقر دم جنيني شديد أو نقص أكسجة، مثل النزف الجنيني الأمومي أو داء الريسوس.
What to doIt is an ominous pattern. Escalate immediately — it does not respond to position or fluids.الإجراء المطلوب — نمط منذر: يُصعَّد الأمر فوراً فهو لا يستجيب للوضعية ولا للسوائل.
Now the error that has killed babies while an apparently normal trace was running: the monitor can pick up the mother’s pulse and record it as the fetal heart.
الآن الخطأ الذي تسبّب في وفاة أطفال بينما كان يجري تسجيل مخطّط يبدو طبيعياً: أن الجهاز قد يلتقط نبض الأمّ ويسجّله كنبض الجنين.
•When it happens — and how to catch it◆ متى يحدث — وكيف يُكتشف
When the fetal heart is hard to detectOr when the baby has died or is severely compromised — exactly when you most need the trace to be real.حين يصعب كشف نبض الجنين — أو حين يكون الطفل قد مات أو متضرّراً بشدّة، أي حين تشتدّ الحاجة إلى أن يكون التخطيط حقيقياً.
In the second stageWhen she is pushing and the transducer shifts.في المرحلة الثانية — حين تدفع الأمّ ويتزحزح المجسّ.
And in maternal tachycardiaA maternal pulse of 130 sits inside the normal fetal range — so it looks entirely plausible.وفي تسرّع قلب الأمّ — نبض الأمّ البالغ ١٣٠ يقع داخل المدى الجنيني الطبيعي فيبدو معقولاً تماماً.
So palpate her pulse WHILE watching the traceIf the two coincide, the monitor is recording her. Use a fetal scalp electrode or ultrasound to confirm, and never assume the machine is right because it is producing a picture.لذا يُجَسّ نبضها أثناء مشاهدة المخطّط — فإن تطابقا فالجهاز يسجّلها هي. ويُستعان بقطب فروة رأس الجنين أو بالموجات فوق الصوتية للتأكيد، ولا يُفترض أبداً أن الجهاز على صواب لمجرّد أنه ينتج صورة.
🚩
Watch out
تنبيه
A fourth category means act now: an acute bradycardia, or a single prolonged deceleration lasting three minutes or more. That is not a trace to keep watching.
فئة رابعة تعني التصرّف الآن: بطء قلب حادّ أو تباطؤ مطوّل منفرد يدوم ثلاث دقائق أو أكثر. وهذا ليس تخطيطاً يُكتفى بمواصلة مراقبته.
🚩
Watch out
تنبيه
With a prolonged deceleration, actively exclude the three accidents — cord prolapse, placental abruption and uterine rupture. No amount of repositioning fixes those.
مع تباطؤ مطوّل يجب استبعاد الحوادث الثلاثة بصورة فعّالة — تدلّي الحبل وانفصال المشيمة وتمزّق الرحم. فلا قدر من إعادة الوضعية يصلحها.
🔑
Memory aid
مفتاح للحفظ
Classify the whole trace as normal, suspicious or pathological rather than reacting to a single deceleration — and re-classify at intervals, because a trace that was normal an hour ago is not evidence about now.
يُصنَّف التخطيط كلّه كطبيعي أو مشبوه أو مرضي ولا يُستجاب لتباطؤ منفرد — ويُعاد التصنيف بفواصل، فالتخطيط الذي كان طبيعياً قبل ساعة ليس دليلاً على الحال الآن.
🚩
Watch out
تنبيه
A sinusoidal pattern is a smooth regular wave with no variability and no accelerations. It suggests severe fetal anaemia, it is pathological, and it is escalated immediately.
النمط الجيبي موجة ملساء منتظمة بلا تغيّرية ولا تسارعات. ويوحي بفقر دم جنيني شديد وهو مرضي ويُصعَّد فوراً.
🚩
Watch out
تنبيه
The monitor can record the mother's pulse as the fetal heart. Palpate and record her pulse alongside the trace and compare the two — babies have died while an apparently normal trace was running.
الجهاز قد يسجّل نبض الأمّ كقلب الجنين. يُجَسّ نبضها ويُسجَّل إلى جانب التخطيط ويُقارَن بينهما — فقد مات أطفال بينما كان تخطيط يبدو طبيعياً يجري.
⭐
Key point
نقطة أساسية
A maternal pulse recorded as a fetal heart accelerates with contractions as she pushes — the opposite of the fetal pattern, and the clue people miss.
نبض الأمّ المسجَّل كقلب جنين يتسارع مع التقلّصات وهي تدفع — عكس النمط الجنيني وهو الدليل الذي يُغفِله الناس.
⭐
Key point
نقطة أساسية
Continuous monitoring flags many well babies, restricts mobility and is not a guarantee — which is why intermittent auscultation is appropriate in an uncomplicated labour.
المراقبة المستمرّة تثير القلق بشأن كثير من الأطفال السليمين وتقيّد الحركة وليست ضماناً — ولهذا يكون الإصغاء المتقطّع مناسباً في مخاض غير معقّد.
8
5.7 · Acting on a Concerning Trace, and Induction٥٫٧ · التصرّف وفق تخطيط مقلق والتحريض
When a trace becomes concerning, act on the reversible causes first, in a fixed order — several of them work within minutes.
حين يصير مخطّط مقلقاً يُتعامَل مع الأسباب القابلة للعكس أولاً بترتيب ثابت — فعدّة منها تعمل خلال دقائق.
1
Change her position
Left lateral first — relieves aortocaval compression and improves placental flow.
تغيير وضعيتها — جانبية يسرى أولاً: تزيل ضغط الأبهر والأجوف وتحسّن جريان الدم إلى المشيمة.
2
Check her blood pressure
Treat hypotension — especially after an epidural.
فحص ضغطها — وعلاج هبوط الضغط خاصّةً بعد فوق الجافية.
3
Give intravenous fluids
If she is hypotensive or dehydrated.
إعطاء سوائل وريدية — إن كانت هابطة الضغط أو مصابة بالجفاف.
4
Stop or reduce the oxytocin
Uterine hyperstimulation is a common and correctable cause — the uterus is not relaxing enough between contractions for the placenta to refill. Stop the infusion if the trace is pathological or shows late decelerations; reduce it if the trace is only suspicious.
إيقاف الأوكسيتوسين أو تقليله — فرط التنبيه الرحمي سبب شائع قابل للتصحيح: فالرحم لا يرتخي بما يكفي بين التقلّصات لكي تعيد المشيمة امتلاءها. ويُوقَف التسريب إن كان التخطيط مرضياً أو ظهرت تباطؤات متأخّرة، ويُقلَّل إن كان التخطيط مشبوهاً فحسب.
5
Exclude cord prolapse
Especially if the membranes have just ruptured — vaginal examination.
And prepare for expedited birth if it does not resolve.
استدعاء المساعدة — والاستعداد لولادة معجّلة إن لم تُحَلّ المشكلة.
Induction of labour is starting labour artificially, and the method depends on the cervix.
تحريض المخاض بدء المخاض اصطناعياً والطريقة تعتمد على العنق.
•The methods, in the order they are usually used◆ الطرق بالترتيب الذي تُستخدم به عادةً
Membrane sweepA finger swept around the cervix to separate the membranes — may start labour without formal induction.كنس الأغشية — يُمرَّر إصبع حول العنق لفصل الأغشية، وقد يبدأ المخاض بلا تحريض رسمي.
ProstaglandinRipens an unfavourable cervix. Fetal monitoring after insertion.البروستاغلاندين — يُنضج عنقاً غير مواتٍ مع مراقبة جنينية بعد الإدخال.
AmniotomyArtificial rupture of the membranes, once the cervix is favourable. Auscultate the fetal heart immediately afterwards — cord prolapse.بضع الأغشية — تمزيق الأغشية اصطناعياً بعد أن يصير العنق مواتياً؛ ويُصغى لقلب الجنين فوراً بعده بسبب خطر تدلّي الحبل.
Oxytocin infusionTitrated against the contraction pattern, never against the pain. Continuous monitoring is mandatory.تسريب الأوكسيتوسين — يُعايَر مقابل نمط التقلّص لا مقابل الألم، والمراقبة المستمرّة إلزامية.
•The two risks of induction that a nurse manages◆ خطران من مخاطر التحريض يتولّى التمريض التعامل معهما
Uterine hyperstimulationMore than five contractions in ten minutes, or contractions lasting over two minutes, or insufficient relaxation between them. The placenta refills between contractions — no gap means no oxygen. Stop the oxytocin (or reduce it if the trace is only suspicious), turn her left, give fluids, and call for help.فرط التنبيه الرحمي — أكثر من خمسة تقلّصات في عشر دقائق أو تقلّصات تدوم أكثر من دقيقتين أو ارتخاء غير كافٍ بينها. وتعيد المشيمة امتلاءها بين التقلّصات — فبلا فاصل لا أكسجين. يُوقَف الأوكسيتوسين (أو يُقلَّل إن كان التخطيط مشبوهاً فحسب)، وتُدار المرأة إلى جهة اليسار، وتُعطى السوائل، ويُستدعى العون.
Failed induction and cascadeInduction may not succeed and can bring further interventions (an oxytocin infusion, continuous monitoring, an epidural, an assisted birth), so the decision is made with her, with the reason explained — not presented as routine.التحريض الفاشل والشلّال — قد لا ينجح التحريض وقد يستتبع تدخّلات أخرى (تسريب الأوكسيتوسين والمراقبة المستمرّة وفوق الجافية والولادة الآلية)، لذا يُتَّخذ القرار مع المرأة مع شرح السبب ولا يُقدَّم كإجراء روتيني.
🔑
Memory aid
مفتاح للحفظ
LION for intrauterine resuscitation: Left lateral, Intravenous fluids, Oxygen (only if she is hypoxic or per protocol), Notify and stop the oxytocin.
الاختصار LION للإنعاش داخل الرحم: الجانب الأيسر وسوائل وريدية وأكسجين (فقط عند نقص أكسجة الأم أو بحسب البروتوكول المعتمد) وإبلاغ وإيقاف الأوكسيتوسين.
🚩
Watch out
تنبيه
The first action for any concerning deceleration is to turn her onto her left side. It costs nothing, takes seconds and frequently resolves the pattern by itself.
أول إجراء لأيّ تباطؤ مقلق تقليبها على جانبها الأيسر. فهو لا يكلّف شيئاً ويستغرق ثوانيَ ويحلّ النمط بنفسه كثيراً.
🚩
Watch out
تنبيه
Late decelerations in a woman on oxytocin mean the oxytocin is stopped — not reduced, and not continued while someone is found.
التباطؤات المتأخّرة لدى امرأة على أوكسيتوسين تعني إيقاف الأوكسيتوسين — لا تقليله ولا مواصلته حتى يُوجَد أحد.
🚩
Watch out
تنبيه
Continuous fetal monitoring is mandatory while oxytocin runs, and contractions are assessed by palpation as well as by the trace. Oxytocin also has an antidiuretic effect, so fluid balance is recorded.
المراقبة الجنينية المستمرّة إلزامية أثناء جريان الأوكسيتوسين وتُقيَّم التقلّصات بالجسّ كما بالتخطيط. وللأوكسيتوسين أثر مضادّ للإدرار فيُسجَّل توازن السوائل.
9
5.8 · The Emergencies of Labour٥٫٨ · طوارئ المخاض
Cord prolapse is the cord descending through the cervix ahead of or beside the presenting part. It is an emergency because the cord is compressed between the presenting part and the pelvis, cutting off the baby’s oxygen.
تدلّي الحبل نزول الحبل عبر العنق أمام الجزء المتقدّم أو بجانبه. وهو حالة إسعافية لأن الحبل يُضغَط بين الجزء المتقدّم والحوض فيقطع أكسجين الطفل.
1
Call for help — immediately
Put out the obstetric emergency call. Do not leave her to go for help.
استدعاء المساعدة فوراً — يُطلَق نداء الطوارئ الولادي ولا تُترَك المرأة لتذهب لطلب المساعدة.
2
Relieve the pressure
With a gloved hand in the vagina, push the presenting part upwards and off the cord, and keep it there until told to stop.
إزالة الضغط — بيد مقفّزة داخل المهبل يُدفَع الجزء المتقدّم للأعلى وبعيداً عن الحبل ويُبقى كذلك حتى يُطلَب التوقّف.
3
Change her position
Knee-chest, or exaggerated Sims, or head-down — to use gravity to lift the presenting part off the cord.
تغيير وضعيتها — الركبة للصدر أو سيمز المبالغ فيها أو الرأس للأسفل — لاستخدام الجاذبية في رفع الجزء المتقدّم عن الحبل.
4
Fill the bladder if instructed
A filled bladder lifts the presenting part — done on instruction, per your protocol.
تُملأ المثانة إن صدرت تعليمات بذلك — فالمثانة الممتلئة ترفع الجزء المتقدّم، ويُنفَّذ ذلك بتعليمات وبحسب البروتوكول.
5
Prepare for immediate birth
Usually caesarean — this is a time-critical delivery.
الاستعداد لولادة فورية — قيصرية عادةً: وهذه ولادة حرجة زمنياً.
•What must NOT be done◆ ما يجب ألّا يُفعَل
Do not push the cord back insideHandling it causes vasospasm and worsens the compromise.لا يُعاد الحبل إلى الداخل — فالتعامل معه يسبّب تشنّجاً وعائياً ويزيد حالة الجنين سوءاً.
Do not leave her to fetch helpPress the emergency call, or send someone else.لا تُترَك المرأة لجلب المساعدة — يُضغَط زرّ نداء الطوارئ أو يُرسَل شخص آخر.
If the cord is outside the vaginaHandle it minimally, keep it warm and moist with warm saline swabs — cold also causes vasospasm.إن كان الحبل خارج المهبل — يُتعامَل معه بأدنى حدّ ويُبقى دافئاً رطباً بكِمادات من محلول ملحي دافئ — فالبرد أيضاً يسبّب تشنّجاً وعائياً.
Shoulder dystocia is the head being born but the anterior shoulder failing to deliver behind the pubic bone. It is recognised by the turtle sign — the head delivering and then retracting against the perineum — and by the shoulders not following with the next contraction.
عسر ولادة الكتف هو ولادة الرأس مع فشل الكتف الأمامي في الخروج خلف عظم العانة. ويُميَّز بعلامة السلحفاة — خروج الرأس ثم انسحابه على العجان — وبعدم لحاق الكتفين بالرأس مع التقلّص التالي.
1
Call for help
This needs more hands, immediately.
استدعاء المساعدة — يلزم مزيد من الأيدي فوراً.
2
McRoberts — the first manoeuvre
Hyperflex her hips onto her abdomen. It rotates the pelvis and flattens the sacrum, and it is often sufficient on its own.
مناورة ماكروبرتس أولاً — فرط ثني وركيها على بطنها: يُدير الحوض ويسطّح العجز، وهو كافٍ وحده في كثير من الأحيان.
3
Suprapubic pressure
Applied above the pubic bone — not fundal — to push the shoulder into the oblique.
ضغط فوق العانة — لا على القاع: لدفع الكتف إلى القطر المائل.
4
Then internal manoeuvres
By the accoucheur, per your protocol.
ثم المناورات الداخلية — يجريها المولّد بحسب البروتوكول المعتمد.
5
Record the time from head to body
This is a documented, timed emergency.
تسجيل الزمن من الرأس إلى الجسم — فهذه حالة إسعافية موثّقة وموقّتة.
•The two prohibitions in shoulder dystocia◆ المحظوران في عسر ولادة الكتف
Never apply fundal pressureIt worsens the impaction by driving the shoulder harder against the pubic bone — and it risks uterine rupture. Suprapubic, never fundal.لا يُضغَط على قاع الرحم أبداً — فهو يزيد الانحشار سوءاً بدفع الكتف بقوّة أكبر نحو عظم العانة، ويخاطر بتمزّق الرحم. الضغط فوق العانة لا على القاع أبداً.
Do not pull harder on the headTraction causes brachial plexus injury. The manoeuvres change the geometry; force does not.لا يُسحَب الرأس بقوّة أكبر — فالشدّ يسبّب إصابة الضفيرة العضدية. فالمناورات هي التي تغيّر الهندسة لا القوّة.
Amniotic fluid embolism is rare, unpredictable and often fatal: amniotic fluid enters the maternal circulation and provokes a catastrophic reaction. It presents with sudden collapse — breathlessness, hypotension, hypoxia, seizures, cardiac arrest — typically followed by massive haemorrhage from coagulopathy. There is no specific treatment: the response is immediate resuscitation, massive transfusion protocol, and the whole team. What a nurse contributes is recognition and speed.
الانصمام بالسائل الأمنيوسي نادر وغير متوقّع وقاتل غالباً: يدخل السائل الأمنيوسي الدوران الأمومي ويثير تفاعلاً كارثياً. ويتظاهر بانهيار مفاجئ — ضيق نفس وهبوط ضغط ونقص أكسجة واختلاجات وتوقّف قلب — يتبعه عادةً نزف هائل من اعتلال التخثّر. ولا علاج نوعي: فالاستجابة إنعاش فوري وبروتوكول نقل الدم الهائل والفريق كلّه. وما تسهم به الممرّضة هو التعرّف على الحالة والسرعة.
🔑
Memory aid
مفتاح للحفظ
Cord prolapse: call for help, push the presenting part off the cord and keep it there, knee-chest or head-down, oxygen (only if she is hypoxic or per protocol), stop oxytocin, prepare for immediate caesarean.
تدلّي الحبل: استدعاء المساعدة ودفع الجزء المتقدّم بعيداً عن الحبل وإبقاؤه هناك وركبة-صدر أو رأس لأسفل وأكسجين (فقط عند نقص أكسجة الأم أو بحسب البروتوكول المعتمد) وإيقاف الأوكسيتوسين والتحضير لقيصرية فورية.
🚩
Watch out
تنبيه
Do not push the cord back inside — handling causes vasospasm. Do not leave her to fetch help. If the cord is outside, handle it minimally and keep it warm and moist.
لا يُدفَع الحبل إلى الداخل — فالمناولة تسبّب تشنّجاً وعائياً. ولا تُترَك المرأة لجلب المساعدة. وإن كان الحبل خارجاً فيُناوَل بأدنى ما يمكن ويُبقى دافئاً رطباً.
🚩
Watch out
تنبيه
In shoulder dystocia, fundal pressure is absolutely contraindicated — it worsens the impaction and risks uterine rupture. Suprapubic pressure, never fundal.
في عسر ولادة الكتف الضغط على القاع ممنوع منعاً باتّاً — فهو يسوّئ الانحشار ويخاطر بتمزّق الرحم. الضغط فوق العانة لا على القاع أبداً.
🔑
Memory aid
مفتاح للحفظ
McRoberts is the first manoeuvre: hyperflexion of the mother's hips onto her abdomen, combined with suprapubic pressure. It often resolves the dystocia on its own.
ماكروبرتس المناورة الأولى: فرط انثناء وركي الأمّ على بطنها مع الضغط فوق العانة. وتحلّ العسر وحدها غالباً.
⭐
Key point
نقطة أساسية
Note the time in shoulder dystocia — the interval to delivery determines the outcome and must be documented. Do not pull hard on the head, which causes brachial plexus injury.
يُسجَّل الوقت في عسر ولادة الكتف — فالفاصل حتى الولادة يحدّد المآل ويجب توثيقه. ولا يُسحَب الرأس بقوّة فذلك يسبّب إصابة الضفيرة العضدية.
10
5.9 · The Other Things That Go Wrong٥٫٩ · الأمور الأخرى التي تسوء
Vasa praevia belongs alongside the bleeding of Chapter 04, because the discrimination changes everything: fetal blood vessels run unsupported through the membranes across the cervix, and when the membranes rupture the vessels tear.
الأوعية المتقدّمة تنتمي إلى جانب نزف الفصل الرابع فالتمييز يغيّر كلّ شيء: فأوعية دم جنينية تجري غير مدعومة عبر الأغشية فوق العنق وحين تتمزّق الأغشية تتمزّق الأوعية.
🩸Maternal bleeding
Placenta praevia, abruption
The mother loses blood
She has a large circulating volume
She compensates — for a while
نزف أمومي — المشيمة المنزاحة وانفصال المشيمة: الأمّ تفقد الدم ولديها حجم دوراني كبير فتعوّض — لفترة.
الأوعية المتقدّمة — الطفل يفقد الدم وحجمه الكلّي ضئيل: نزف حتى الموت خلال دقائق. نزف غير مؤلم عند التمزّق مع تدهور جنيني مفاجئ = التصرّف فوراً.
•Malpresentation, obstruction and a retained placenta◆ سوء المجيء والانسداد والمشيمة المحتبسة
BreechButtocks or feet presenting — higher risk of cord prolapse because the presenting part fits the cervix poorly. Options: external cephalic version before labour, planned caesarean, or vaginal breech birth by an experienced practitioner.المجيء المقعدي — مجيء الأليتين أو القدمين: خطر أعلى لتدلّي الحبل فالجزء المتقدّم يناسب العنق بسوء. الخيارات: التدوير الرأسي الخارجي (ECV) قبل المخاض، أو قيصرية مخطّط لها، أو ولادة مقعدية مهبلية على يد ممارس خبير.
Transverse or shoulderVaginal birth is not possible — caesarean, and a high cord prolapse risk if the membranes rupture.المجيء المستعرض أو الكتفي — الولادة المهبلية غير ممكنة: قيصرية، مع خطر مرتفع لتدلّي الحبل إن تمزّقت الأغشية.
Obstructed labourFailure to progress despite adequate contractions. Two dangers: uterine rupture, and fistula from prolonged pressure of the head on the soft tissues — a lifelong injury from a labour that was allowed to continue.المخاض المتعسّر — عدم التقدّم رغم تقلّصات كافية. وفيه خطران: تمزّق الرحم، والناسور من الضغط المطوّل للرأس على الأنسجة الرخوة — إصابة تدوم مدى الحياة من مخاض سُمح له بالاستمرار.
Retained placentaNot delivered within the protocol interval. The uterus cannot contract down while it is in place — so the risks are haemorrhage and infection. Meanwhile: rub up a contraction, empty the bladder, keep intravenous access, and prepare for manual removal.المشيمة المحتبسة — لم تخرج ضمن الفاصل الزمني المحدّد في البروتوكول. فالرحم لا يستطيع التقلّص ما دامت في مكانها، والخطران نزف وعدوى. وفي الأثناء: تدليك القاع لإثارة تقلّص، وإفراغ المثانة، والإبقاء على المدخل الوريدي، والاستعداد للنزع اليدوي.
Note the recurring theme: a full bladder appears as a correctable cause in delayed progress, in a deviated fundus, in a retained placenta and in postpartum haemorrhage. It is the cheapest intervention in obstetrics.
يُلاحَظ الموضوع المتكرّر: أن المثانة الممتلئة تظهر كسبب قابل للتصحيح في تأخّر التقدّم وفي القاع المنحرف وفي المشيمة المحتبسة وفي النزف التالي للولادة. وهي أرخص تدخّل في التوليد.
🚩
Watch out
تنبيه
In vasa praevia the blood is the baby's, not the mother's, so a modest amount can exsanguinate it within minutes. The clue is a distressed baby with a completely well mother.
في الأوعية المتقدّمة الدم للطفل لا للأمّ، فكمّية متواضعة قد تستنزفه خلال دقائق. والدليل جنين في كرب وأمّ بخير تماماً.
⭐
Key point
نقطة أساسية
A breech presentation carries a higher risk of cord prolapse, because the presenting part fits the cervix poorly.
المجيء المقعدي يحمل خطراً أعلى لتدلّي الحبل لأن الجزء المتقدّم يناسب العنق بسوء.
🚩
Watch out
تنبيه
Obstructed labour risks uterine rupture and, through prolonged pressure on the soft tissues, an obstetric fistula. A partogram that has flattened is escalated rather than watched.
المخاض المتعسّر يخاطر بتمزّق الرحم وعبر الضغط المطوّل على الأنسجة الرخوة بناسور توليدي. والمخطّط الذي استوى يُصعَّد لا يُراقَب.
⭐
Key point
نقطة أساسية
With a retained placenta, ensure the bladder is empty — a full bladder prevents the uterus contracting. Do not apply cord traction without counter-pressure.
مع مشيمة محتبسة يُتأكَّد من فراغ المثانة — فالممتلئة تمنع تقلّص الرحم. ولا يُطبَّق شدّ الحبل دون ضغط مضادّ.
⭐
Key point
نقطة أساسية
Maternal fever in labour may be chorioamnionitis or epidural-related, and the two are indistinguishable at the bedside. Investigate rather than attribute, and inform the neonatal team.
حمّى الأمّ في المخاض قد تكون التهاب مشيماء أو مرتبطةً بفوق الجافية وهما غير قابلتين للتمييز عند السرير. يُستقصى السبب ولا يُنسَب إلى أحدهما ويُبلَّغ فريق الولدان.
11
5.10 · The Third Stage, Operative Birth and the Local Setting٥٫١٠ · المرحلة الثالثة والولادة العملياتية والسياق المحلّي
💉Active management
A uterotonic with or just after the birth
Delayed clamping and cutting of the cord (at least a minute)
Controlled cord traction to deliver the placenta
Shortens the third stage and substantially reduces postpartum haemorrhage
Recommended as routine
التدبير الفعّال — مقبّض للرحم مع الولادة أو بعدها مباشرةً، وتأخير ربط الحبل وقطعه (دقيقة على الأقلّ)، وشدّ حبل مضبوط لإخراج المشيمة: يقصّر المرحلة الثالثة ويقلّل النزف التالي للولادة جوهرياً، وهو الموصى به كإجراء روتيني.
⏳Physiological management
No uterotonic
Cord left to stop pulsating
Placenta delivered by maternal effort and gravity
Longer third stage; higher blood loss
A choice she may make, with the difference explained
التدبير الفيزيولوجي — بلا مقبّض للرحم، ويُترك الحبل حتى يتوقّف النبض، وتخرج المشيمة بجهد الأمّ وبالجاذبية: مرحلة ثالثة أطول وفقد دم أعلى؛ وهو خيار يحقّ للمرأة اتخاذه مع شرح الفرق.
The signs of placental separation are three, and they are examined.
علامات انفصال المشيمة ثلاث وتُفحَص.
A gush of bloodfrom the vaginaدفقة دم من المهبل
Cord lengthensat the vulvaالحبل يطول عند الفرج
Uterus changesfirmer, more globular, rises in the abdomenالرحم يتغيّر — أمتن وأكثر كروية ويرتفع في البطن
Perineal trauma is graded, and the grade determines the repair and the follow-up.
Extends through the sphincter into the rectal mucosa.
الدرجة الرابعة — تمتدّ عبر المصرّة إلى مخاطية المستقيم.
Third and fourth degree tears need specific follow-up — they carry a real risk of long-term incontinence, so they need repair by someone trained for it, antibiotics, stool softeners, physiotherapy, and a follow-up appointment that is arranged rather than offered. A woman who develops incontinence after a tear that was never followed up is a preventable and common outcome.
التمزّقان من الدرجة الثالثة والرابعة يحتاجان متابعةً محدّدة — فهما يحملان خطراً حقيقياً لسلس طويل الأمد، فيحتاجان إصلاحاً من مدرَّب عليه ومضادات حيوية وملّينات وعلاجاً طبيعياً وموعد متابعة مُرتَّباً لا معروضاً. والمرأة التي تصاب بسلس بعد تمزّق لم يُتابَع نتيجة قابلة للمنع وشائعة.
•Operative birth◆ الولادة العملياتية
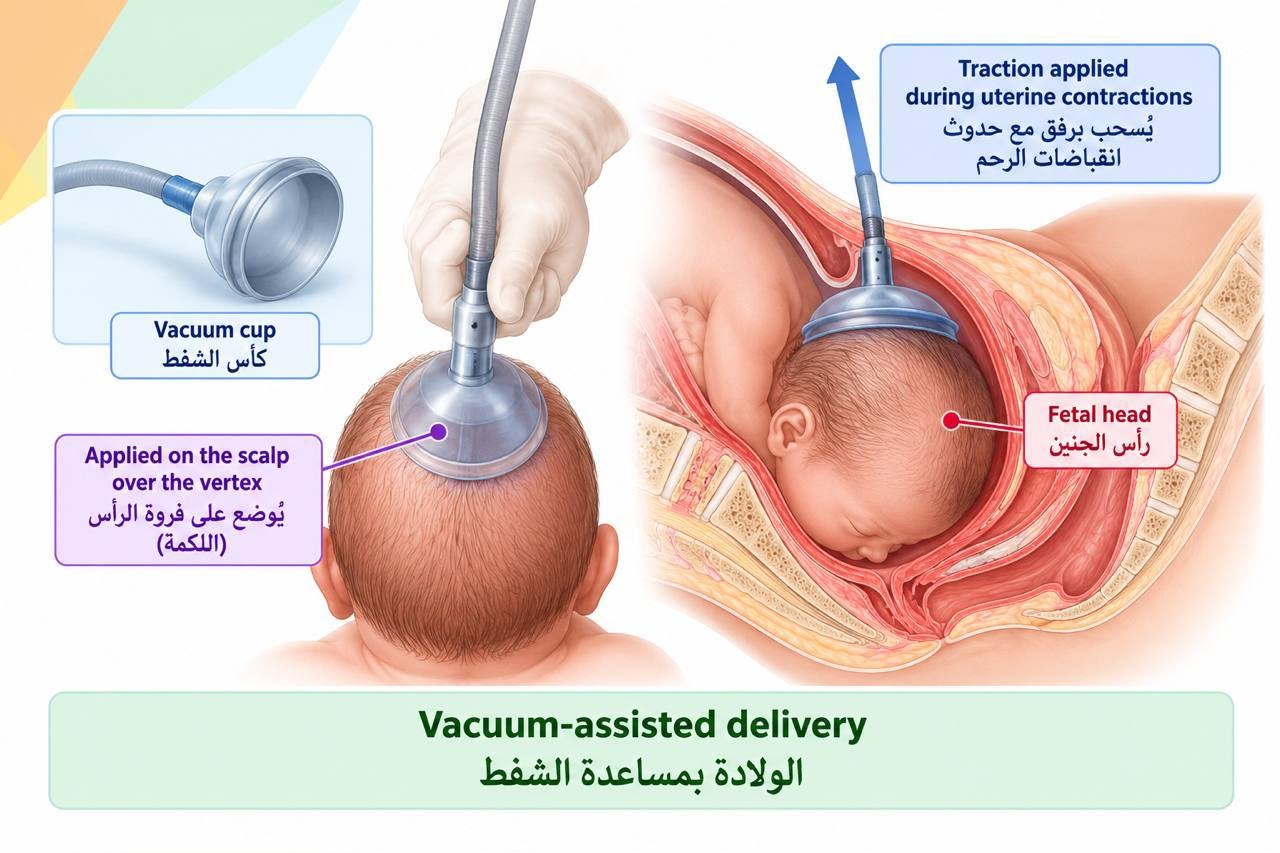
Instrumental — forceps or vacuumFor delay in the second stage, fetal compromise, or to shorten the second stage for a maternal reason. The nursing role is preparation, position, bladder emptying, and support — and afterwards, watching for perineal trauma and postpartum haemorrhage.آلية — ملقط أو شفط: عند تأخّر المرحلة الثانية أو تعرّض الجنين للخطر أو لتقصير المرحلة الثانية لسبب أمومي. والدور التمريضي التحضير والوضعية وإفراغ المثانة والدعم — وبعدها ترصُّد رضّ العجان والنزف التالي للولادة.
CaesareanThe nursing role spans preparation, theatre care and recovery — and the postnatal care of Chapter 06 applies unchanged, with the addition of wound care and earlier mobilisation for thrombosis risk.قيصرية — الدور التمريضي يمتدّ من التحضير إلى رعاية غرفة العمليات والتعافي — وتنطبق الرعاية بعد الولادة الواردة في الفصل السادس كما هي، مع إضافة العناية بالجرح والتحريك المبكّر بسبب خطر الخثار.
Skin to skin still appliesIncluding in theatre where it is safe to do so — it is not a luxury reserved for vaginal birth.التلامس الجلدي ما زال ينطبق — بما في ذلك في غرفة العمليات حيث يكون آمناً؛ فهو ليس ترفاً محصوراً بالولادة المهبلية.
•Three points about this setting◆ ثلاث نقاط عن هذا السياق
A female practitionerMany women wish to be attended by a woman in labour. Where the service can accommodate that it should — and where it cannot, say so honestly and early, not at the door of the room.ممارِسة أنثى — كثيرات من النساء يرغبن في أن تتولّى رعايتهنّ امرأة أثناء المخاض. وحيث تستطيع الخدمة تلبية ذلك فينبغي لها أن تفعل — وحيث لا تستطيع يُقال ذلك بصدق وفي وقت مبكّر لا عند باب الغرفة.
Privacy and coveringKeep her covered except where exposure is necessary, and manage who is in the room — a labour room with unnecessary people in it is a barrier to her progress, not only to her dignity.الخصوصية والتغطية — تُبقى المرأة مغطّاة إلا حيث يلزم التعرّض، ويُضبط من يوجد في الغرفة — فغرفة المخاض التي فيها أشخاص غير ضروريين عائق أمام تقدّمها لا أمام كرامتها فحسب.
Religious observance at birthMany families wish the adhan recited into the newborn’s right ear and the iqamah into the left shortly after birth, and some observe tahnik — placing something sweet such as softened date on the palate. Ask, allow time and space for it, and do not let routine tasks displace it.الالتزام الديني عند الولادة — ترغب أسر كثيرة في أن يُؤذَّن في أذن المولود اليمنى وتُقال الإقامة في اليسرى بُعيد الولادة، ويحرص بعضها على التحنيك — وضع شيء حلو كتمر طريّ على الحنك. يُسأل عن ذلك، ويُتاح له الوقت والمكان، ولا تُترك المهامّ الروتينية تزيحه.
These are not concessions. A birth is a religious and family event as much as a clinical one, and a team that makes room for that is not being indulgent — it is delivering the care correctly.
هذه ليست تنازلات. فالولادة حدث ديني وعائلي بقدر ما هو حدث سريري، والفريق الذي يُفسح المجال لذلك ليس متساهلاً — بل يقدّم الرعاية على الوجه الصحيح.
🔑
Memory aid
مفتاح للحفظ
Signs of placental separation: a gush of blood, lengthening of the cord, and the uterus becoming firmer, more globular and rising in the abdomen.
علامات انفصال المشيمة: دفقة دم واستطالة الحبل والرحم يصير أصلب وأكثر كروية ويرتفع في البطن.
🚩
Watch out
تنبيه
Third and fourth degree tears carry a risk of faecal incontinence that women are too embarrassed to report. Ask directly at the postnatal check rather than waiting for disclosure.
تمزّقات الدرجتين الثالثة والرابعة تحمل خطر سلس براز تخجل النساء من الإبلاغ عنه. يُسأل مباشرةً في الفحص النفاسي ولا يُنتظَر الإفصاح.
⭐
Key point
نقطة أساسية
Weigh swabs and pads rather than estimating blood loss by eye — visual estimation consistently underestimates.
تُوزَن الشاشات والفوط ولا يُقدَّر فقد الدم بالعين — فالتقدير البصري يقلّل من المقدار باتّساق.
⭐
Key point
نقطة أساسية
Ask before the birth what religious observances the family would like — the adhan, and in some families tahnik — and record it, so it happens without anyone having to ask in the middle of it.
يُسأل قبل الولادة عن الشعائر التي ترغب فيها الأسرة — الأذان وفي بعض الأسر التحنيك — وتُسجَّل لتحدث دون أن يضطرّ أحد للطلب في وسطها.
🚩
Watch out
تنبيه
Controlled cord traction is applied only with counter-pressure on the uterus. Traction without it risks uterine inversion.
الشدّ المضبوط للحبل يُطبَّق فقط مع ضغط مضادّ على الرحم. فالشدّ دونه يخاطر بانقلاب الرحم.
Vacuum-assisted delivery — a chignon on the scalp is expected, but report any swelling that crosses suture linesالولادة بمساعدة الشفّاط — يُتوقّع تورّم فروة الرأس (الكعكة)، لكن يُبلَّغ عن أيّ تورّم يعبر خطوط الدروزAL-FAHAD illustration
12
5.11 · The Second Stage in Detail, and the First Minutes of Life٥٫١١ · المرحلة الثانية بالتفصيل والدقائق الأولى من الحياة
⏸️Passive second stage
Full dilatation without an involuntary urge to push
The head is still descending
Directed pushing here simply exhausts her
Allow time — especially with an epidural, where the urge is blunted
المرحلة الثانية السلبية — توسّع تامّ بلا رغبة لا إرادية في الدفع؛ والرأس ما زال ينزل. الدفع الموجَّه هنا يُنهك المرأة فقط؛ ويُتاح الوقت — خاصّةً مع فوق الجافية حيث تخفّ الرغبة.
▶️Active second stage
She has the urge, or the head is visible
Spontaneous pushing with her own urge beats counted directed pushing
Upright positions use gravity and open the outlet
Watch the perineum and the fetal heart after every contraction
المرحلة الثانية النشطة — توجد الرغبة في الدفع أو يكون الرأس مرئياً. الدفع التلقائي مع رغبة المرأة نفسها يفوق الدفع الموجَّه المعدود. والوضعيات المنتصبة تستخدم الجاذبية وتفتح المخرج. ويُرصد العجان وقلب الجنين بعد كلّ تقلّص.
The first minutes after birth follow a fixed order, and the ordering is the point.
الدقائق الأولى بعد الولادة تتبع ترتيباً ثابتاً والترتيب هو المقصد.
1
Dry the baby immediately, remove wet linen
The single most important action to prevent heat loss — a wet newborn loses heat very fast, and cold worsens everything else.
تجفيف الطفل فوراً وإزالة البياضات المبتلّة — أهمّ إجراء منفرد لمنع فقد الحرارة: فالوليد المبتلّ يفقد الحرارة بسرعة كبيرة والبرد يزيد كلّ شيء آخر سوءاً.
2
Assess breathing, tone and colour
As you dry — drying is itself the first stimulation.
تقييم التنفّس والتوتّر واللون — أثناء التجفيف، فالتجفيف نفسه أول تنبيه.
3
Skin to skin with the mother
Naked baby on her bare chest, covered together — the best thermal care there is, and it starts feeding.
تماسّ جلدي مع الأمّ — الطفل عارياً على صدرها العاري ويُغطّيان معاً: أفضل رعاية حرارية موجودة وهو يبدأ الرضاعة.
4
Delayed cord clamping
At least a minute, or until the cord stops pulsating — unless he needs immediate resuscitation. It raises his iron stores for months.
تأخير ربط الحبل — دقيقة على الأقلّ أو حتى يتوقّف النبض، ما لم يحتج المولود إلى إنعاش فوري: يرفع مخزون حديده أشهراً.
5
First feed within the first hour
The window when he is most alert.
أول رضعة خلال الساعة الأولى — النافذة التي يكون فيها في أشدّ يقظته.
6
Then the routine tasks
Weighing, measuring and vitamin K can wait. The first hour cannot be repeated.
ثم المهامّ الروتينية — الوزن والقياس وفيتامين ك تنتظر. فالساعة الأولى لا تُعاد.
•The checks that must happen BEFORE anyone moves◆ الفحوص التي يجب أن تتمّ قبل أن يتحرّك أحد
Identification bandsApplied while the baby is still with the mother, checked against her details with her present and awake enough to confirm them.أساور التعريف — تُوضَع والطفل ما زال مع أمّه وتُفحَص مقابل بياناتها بحضورها وهي مستيقظة بما يكفي لتأكيدها.
The details recordedTime of birth, sex, condition at birth, and who was present.التفاصيل المسجّلة — وقت الولادة والجنس والحالة عند الولادة ومن كان حاضراً.
A baby is never carried looseHe is transported in his cot, including for short distances — and never left on a bed or a surface.الطفل لا يُحمَل سائباً أبداً — يُنقَل في سريره حتى لمسافات قصيرة، ولا يُترك أبداً على سرير أو سطح.
Finally, the person with her. Continuous support in labour from a companion of her choosing is one of the few interventions in maternity care that is free, has no side effects, and improves nearly every outcome measured — shorter labour, less analgesia, fewer operative births, and a better experience. It should be facilitated rather than tolerated.
وأخيراً الشخص معها. فالدعم المستمرّ في المخاض من مرافِق من اختيارها أحد التدخّلات القليلة في رعاية الأمومة التي هي مجّانية وبلا آثار جانبية وتحسّن كلّ نتيجة مقيسة تقريباً — مخاض أقصر وتسكين أقلّ وولادات جراحية أقلّ وتجربة أفضل. وينبغي تيسيره لا احتماله.
⭐
Key point
نقطة أساسية
Passive second stage is full dilatation without an urge to push. Directing a woman to push then exhausts her against a head that has not descended — let it happen, particularly with an epidural.
المرحلة الثانية السلبية توسّع تامّ دون رغبة بالدفع. وتوجيه المرأة للدفع حينها يُنهكها مقابل رأس لم ينزل — يُترك ليحدث خاصّةً مع التخدير فوق الجافية.
🚩
Watch out
تنبيه
Dry the baby immediately and remove the wet linen. It is the single most important action to prevent heat loss, and a cold baby consumes glucose and oxygen it cannot spare.
يُجفَّف الطفل فوراً وتُنزَع البياضات المبلّلة. فهو أهمّ إجراء منفرد لمنع فقد الحرارة والطفل البارد يستهلك غلوكوزاً وأكسجيناً لا يستطيع بذلهما.
⭐
Key point
نقطة أساسية
Skin to skin stabilises temperature, heart rate, breathing and blood glucose and improves breastfeeding. It is not interrupted for routine weighing, measuring or bathing.
التماسّ الجلدي يثبّت الحرارة والنبض والتنفّس وسكّر الدم ويحسّن الرضاعة. ولا يُقطَع لوزن أو قياس أو استحمام روتيني.
🚩
Watch out
تنبيه
Apply identification bands while the baby is still with the mother, reading the details aloud with her present. Misidentification is preventable only at this moment.
تُوضَع أساور التعريف والطفل ما زال مع أمّه مع قراءة البيانات بصوت مسموع بحضورها. فسوء التعريف قابل للمنع في هذه اللحظة فقط.
⭐
Key point
نقطة أساسية
Continuous support from a companion of her choosing is free, has no side effects and improves nearly every outcome. Facilitate the birth partner rather than tolerate them.
الدعم المستمرّ من مرافق تختاره مجاني وبلا آثار جانبية ويحسّن كلّ مآل تقريباً. يُيسَّر أمر المرافق ولا يُكتفى باحتماله.
13
5.12 · Before Anyone Leaves the Room٥٫١٢ · قبل أن يغادر أحد الغرفة
Once the placenta is delivered it is examined for completeness, and this is a check rather than a formality — a retained fragment causes haemorrhage and infection days later, when she is at home.
بمجرّد خروج المشيمة تُفحَص لاكتمالها وهذا فحص لا شكلية — فالجزء المحتبس يسبّب نزفاً وعدوى بعد أيام وهي في المنزل.
1
The maternal surface
A complete set of cotyledons with no missing segment.
السطح الأمومي — مجموعة فلقات كاملة بلا جزء ناقص.
2
The membranes
Whether they are complete, and whether there is a hole suggesting a retained piece.
الأغشية — هل هي كاملة وهل توجد فتحة توحي بقطعة محتبسة.
3
The cord
Three vessels — two arteries and one vein. A single artery is associated with other anomalies and is reported.
الحبل — ثلاثة أوعية: شريانان ووريد. والشريان الوحيد يرتبط بشذوذات أخرى ويُبلَّغ عنه.
4
Record and report anything abnormal
Do not discard it until it has been seen by whoever needs to see it.
تسجيل أيّ شذوذ والإبلاغ عنه — ولا يُتخلَّص من المشيمة حتى يراها من يحتاج إلى ذلك.
Before she gets up for the first time, remember she is at real risk of fainting — from the blood she has lost, from vasodilation, from not having eaten, and where she has had an epidural, from residual block affecting her legs.
قبل أن تنهض أول مرّة يُتذكَّر أنها في خطر إغماء حقيقي — من الدم الذي فقدته ومن التوسّع الوعائي ومن عدم الأكل وحيث كان لديها فوق الجافية من حصار متبقٍّ يؤثّر على ساقيها.
1
Sit her up first
And let her sit for a few minutes before standing.
إجلاسها أولاً — وتركها جالسة دقائق قبل الوقوف.
2
Check her legs work
Especially after an epidural — test before trusting.
التحقّق من أن ساقيها تعملان — خاصّةً بعد فوق الجافية — ويُختبَر ذلك قبل الاعتماد عليه.
3
Never leave her alone
Not on the first walk, and not in the shower or the toilet.
لا تُترك وحدها أبداً — لا في أول مشي ولا أثناء الاستحمام ولا في المرحاض.
4
Have the call bell in reach
And tell her to use it rather than manage alone.
وضع جرس النداء في متناولها — وإخبارها بأن تستخدمه بدلاً من تدبّر أمرها وحدها.
5
Expect a gush of lochia
Pooled blood drains when she stands — warn her, or she will think she is haemorrhaging.
توقّع دفقة هلابة — الدم المتجمّع يُصرَّف عند وقوفها؛ فتُحذَّر المرأة وإلا ظنّت أنها تنزف.
🚩
Watch out
تنبيه
Retained placental tissue or membranes cause postpartum haemorrhage and infection, sometimes after she has gone home. Examine the placenta deliberately and record the finding explicitly.
احتباس نسيج مشيمي أو أغشية يسبّب نزفاً تالياً للولادة وعدوى وأحياناً بعد ذهابها للمنزل. تُفحَص المشيمة عمداً ويُسجَّل الموجود منها صراحةً.
⭐
Key point
نقطة أساسية
A vessel running to the edge of the membranes and ending abruptly suggests a piece left behind. If the placenta is or may be incomplete, escalate immediately.
وعاء يمتدّ إلى حافّة الأغشية وينتهي فجأةً يوحي بقطعة مُتروكة. وإن كانت المشيمة ناقصة أو قد تكون ناقصة فيُصعَّد الأمر فوراً.
🚩
Watch out
تنبيه
Someone is with her the first time she stands — she is at real risk of fainting from blood loss, vasodilation, not having eaten and residual epidural block.
ينبغي أن يكون أحد معها حين تقف أول مرّة — فهي في خطر حقيقي من الإغماء من فقد الدم وتوسّع الأوعية وعدم الأكل وحصار فوق الجافية المتبقّي.
⭐
Key point
نقطة أساسية
A full bladder raises the risk of haemorrhage and may be hard to feel after an epidural, so bladder care is a scheduled task rather than something to wait for her to mention.
المثانة الممتلئة ترفع خطر النزف وقد يصعب الشعور بها بعد التخدير فوق الجافية، فرعاية المثانة مهمّة مجدولة ولا يُنتظَر أن تذكر المرأة حاجتها إليها.
14
5.13 · The Ordinary Care That Runs Through It٥٫١٣ · الرعاية العادية التي تجري خلاله
Alongside everything dramatic, a set of ordinary measures runs through every labour — and they change outcomes more reliably than most of what is remembered.
إلى جانب كلّ ما هو درامي تجري مجموعة تدابير عادية عبر كلّ مخاض — وهي تغيّر النتائج بموثوقية أكبر من معظم ما يُتذكَّر.
•The ordinary care◆ الرعاية العادية
Eating and drinkingA woman at low risk may have water and light food. Starving her is unhelpful — labour is physically demanding and ketosis makes contractions less effective.الأكل والشرب — يجوز للمرأة المنخفضة الخطر تناول الماء والطعام الخفيف. وتجويعها غير نافع فالمخاض مجهد جسدياً والكيتوز يضعف فعالية التقلّصات.
Bladder careEncourage voiding every few hours and record it — a full bladder obstructs descent and is a correctable cause of delay.رعاية المثانة — يُشجَّع التبوّل كلّ بضع ساعات ويُسجَّل — فالمثانة الممتلئة تعيق النزول وهي سبب قابل للتصحيح للتأخّر.
Mobility and positionUpright, kneeling, all-fours or lateral use gravity and open the outlet. Lying on the back is the worst position — it compresses the vena cava and narrows the pelvis.الحركة والوضعية — الوضعيات المنتصبة أو الراكعة أو على اليدين والركبتين أو الجانبية تستخدم الجاذبية وتفتح المخرج؛ والاستلقاء على الظهر أسوأها — فهو يضغط على الأجوف السفلي ويضيّق الحوض.
Comfort and dignityWarmth, mouth care, a quiet room, and control over who is present.الراحة والكرامة — دفء ورعاية فم وغرفة هادئة وتحكّم بمن يحضر.
1
Handover uses a structured format
And includes not only the clinical picture but her plan, her preferences and what she has been told — a woman who has explained her wishes three times has been failed by the handover, not by her memory.
التسليم يستخدم صيغةً منظّمة — ولا يقتصر على الصورة السريرية بل يشمل خطتها وتفضيلاتها وما قيل لها؛ فالمرأة التي شرحت رغباتها ثلاث مرّات خذلها التسليم لا ذاكرتها.
2
The record is contemporaneous
Written as it happens, timed — not reconstructed afterwards. Labour records are examined more often than most.
السجلّ آني — يُكتَب وقت حدوثه مع تدوين الوقت لا يُعاد بناؤه بعدها؛ فسجلّات المخاض تُدقَّق أكثر من معظم السجلّات.
3
Escalate with a structure and a timeframe
What you want to happen and by when — and again if it does not land.
التصعيد ببنية وإطار زمني — ماذا يُراد أن يحدث ومتى — ويُكرَّر إن لم يُستجَب له.
4
Debrief her afterwards
Especially after an emergency — she will otherwise assemble her own version of what happened, and it is usually worse than the truth.
مراجعة الأحداث معها بعد ذلك — خاصّةً بعد حالة إسعافية، وإلا بنت نسختها الخاصّة لما حدث وهي في الغالب أسوأ من الحقيقة.
Finally, the thing that outlasts everything clinical in this chapter. A woman remembers her birth in detail for the rest of her life — and what she remembers is not the fetal heart trace. It is whether she felt safe, whether she was listened to, whether things were explained, and whether she was treated with kindness.
وأخيراً الشيء الذي يعمّر أطول من كلّ ما هو سريري في هذا الفصل. فالمرأة تتذكّر ولادتها بتفاصيلها بقيّة حياتها — وما تتذكّره ليس مخطّط قلب الجنين. بل هل شعرت بالأمان وهل أُصغي إليها وهل شُرحت لها الأمور وهل عُوملت بلطف.
Those are not additions to good clinical care. In a labour room they are good clinical care, and they cost nothing.
تلك ليست إضافات للرعاية السريرية الجيّدة. ففي غرفة الولادة هي الرعاية السريرية الجيّدة ولا تكلّف شيئاً.
⭐
Key point
نقطة أساسية
Delayed cord clamping — at least a minute unless the baby needs immediate resuscitation — improves the baby's iron stores for months and is standard practice rather than an option.
تأخير ربط الحبل — دقيقة على الأقلّ ما لم يحتج الطفل إنعاشاً فورياً — يحسّن مخزون الطفل من الحديد لأشهر وهو ممارسة قياسية لا خيار.
🚩
Watch out
تنبيه
The Apgar score is a record of the baby's condition, not a trigger for resuscitation. Resuscitation begins on assessment of breathing and heart rate, not on waiting for a score.
درجة أبغار سجلّ لحالة الطفل لا محفّز للإنعاش. فالإنعاش يبدأ بتقييم التنفّس ومعدّل القلب لا بانتظار درجة.
⭐
Key point
نقطة أساسية
Skin-to-skin contact maintains the baby's temperature better than an incubator and supports the first feed. Protect it — routine weighing and measuring can wait.
التماسّ الجلدي يحافظ على حرارة الطفل أفضل من حاضنة ويدعم الرضعة الأولى. ويُحمى ذلك التماسّ — فالوزن والقياس الروتينيان يستطيعان الانتظار.
⭐
Key point
نقطة أساسية
In an emergency allocate a scribe whose only job is to record times, drugs and actions as they happen. Reconstruction afterwards is unreliable, and the timings are exactly what matters.
في الطوارئ يُخصَّص مدوِّن مهمّته الوحيدة تسجيل الأوقات والأدوية والإجراءات. فإعادة البناء بعدها غير موثوقة والتوقيتات بالضبط ما يهمّ.
🚩
Watch out
تنبيه
A woman remembers her birth for the rest of her life, and what she remembers is whether she felt safe and was listened to. A clinically excellent birth can still be experienced as traumatic.
المرأة تتذكّر ولادتها بقية حياتها وما تتذكّره هل شعرت بالأمان وهل أُصغي إليها. والولادة الممتازة سريرياً قد تُعاش كتجربة صادمة.
Test yourselfالاختبار الذاتي
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Loading… جارٍ التحميل…
Medical disclaimer. The content of this platform is for education and exam preparation only. It is not medical advice and does not replace consultation with a qualified physician or other licensed healthcare professional, or current clinical guidelines. Do not use it to diagnose or treat any person.
إخلاء المسؤولية الطبية: محتوى هذه المنصة مخصص للتعليم والتحضير للاختبار فقط، وليس نصيحة طبية، ولا يغني عن استشارة الطبيب المختص أو الممارس الصحي المرخّص، ولا عن الإرشادات السريرية الحالية. ولا يجوز استخدامه لتشخيص أي شخص أو علاجه.